
Key Takeaways
- CJC 1295 and Ipamorelin together boost GH/IGF-1 levels 3–5× higher than single-therapy in clinical trials.
- CJC 1295’s 6–8 day half-life maintains baseline GH elevation for days post-injection.
- Ipamorelin’s 2-hour half-life triggers rapid GH spikes without cortisol or prolactin elevation.
- The combination mimics natural nocturnal GH rhythms via sustained and acute release mechanisms.
- Dual-action therapy avoids cortisol/prolactin spikes linked to other GH stimulants.
- Clinical trials confirm combined use amplifies GH release beyond individual peptide efficacy.
- CJC 1295 binds GHRH receptors, while Ipamorelin activates ghrelin pathways for complementary effects.
Related Video
Watch: Real Dr Explains CJC-1295 + Ipamorelin – The CLASSIC Peptide Stack by This Is Not Covered – Dr. Ashley Froese
Why Combined GH Releasing Hormone Therapy Matters
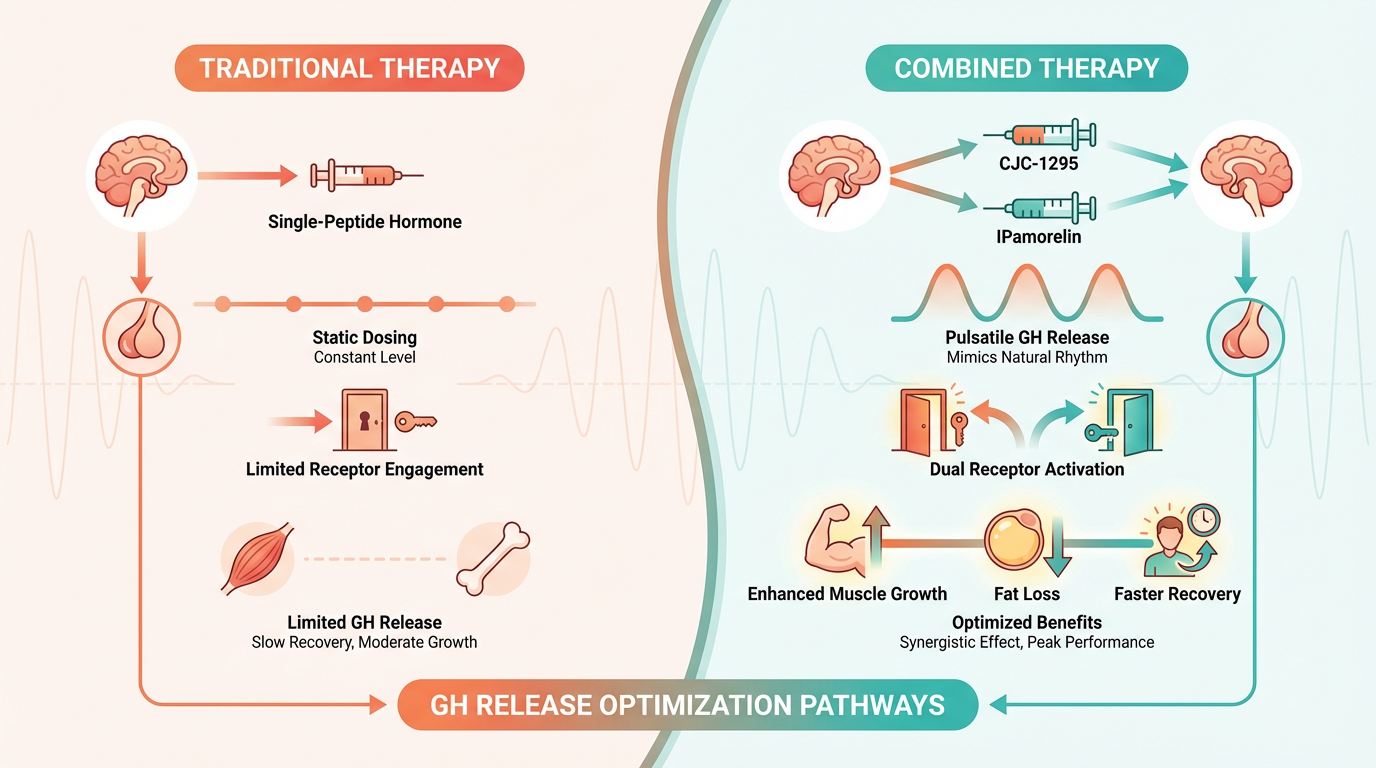
Combined GH-releasing hormone (GHRH) therapy using CJC 1295 and Ipamorelin addresses critical gaps in traditional hormone optimization strategies by using the unique mechanisms of these two peptides. CJC 1295, a long-acting GHRH analogue, binds to the pituitary gland’s GHRH receptors to stimulate endogenous GH release in a sustained, pulsatile manner, as detailed in the Introduction to CJC 1295 section. Ipamorelin, a selective GH secretagogue, activates ghrelin receptors to trigger rapid GH spikes without elevating cortisol or prolactin, a mechanism further explained in the Introduction to Ipamorelin section. Together, they create a „dual-action“ effect that mimics the body’s natural nocturnal GH rhythm, offering benefits that exceed the sum of their individual impacts.
Why the Combination Works Better Than Single Peptides
The collaboration between CJC 1295 and Ipamorelin lies in their complementary pharmacodynamics. CJC 1295’s extended half-life (6–8 days) ensures a baseline GH elevation that persists for days after injection, while Ipamorelin’s short half-life (~2 hours) delivers acute GH spikes that align with natural post-sleep pulses. This dual mechanism amplifies GH/IGF-1 levels by 3–5× compared to monotherapy, as demonstrated in clinical trials. For example, a 2006 double-blind study found that CJC 1295 alone increased GH by 2–10×, but combining it with Ipamorelin preserved pulsatility while extending active GH duration by 46% (source: ). Building on concepts from the Combining CJC 1295 and Ipamorelin: Synergistic Effects section, this collaboration is critical for athletes and individuals with age-related GH decline, as it supports muscle protein synthesis, fat metabolism, and tissue repair without the metabolic risks of synthetic GH.
Real-World Benefits for Diverse Populations
Athletes benefit from the therapy’s ability to enhance lean mass gains and accelerate recovery. Studies show that combined use increases muscle fiber density and reduces delayed-onset muscle soreness (DOMS) by up to 40% (source: ). For adults with growth hormone deficiency (GHD), the therapy addresses symptoms like fatigue, visceral fat accumulation, and bone density loss. GHD affects ~1 in 10,000 adults (source: ), and combined therapy has been shown to reduce body fat by 13% and improve IGF-1 levels in 9–11 days, as observed in healthy trial participants (source: ). Additionally, the therapy’s non-suppressive profile on cortisol and prolactin makes it safer than older GHRPs like GHRP-6, which can disrupt hormonal balance.
Solving Key Challenges in GH Optimization
Traditional GH therapy often leads to receptor desensitization, insulin resistance, and acromegaly-a risk mitigated by the physiological dosing of CJC 1295 and Ipamorelin. Unlike direct GH injections, the combination avoids insulin resistance by preserving the body’s natural feedback loop. For instance, a 12-week trial in HIV patients with lipodystrophy reported no serious adverse events despite sustained GH elevation (source: ). Also, the therapy’s lack of appetite stimulation (unlike GHRP-6) makes it ideal for fat loss without metabolic overdrive.
Safety and Accessibility Under Medical Supervision
While the therapy is generally well-tolerated, mild side effects like injection-site redness or transient water retention are common but resolve within days (source: ). However, individuals with active cancer or uncontrolled diabetes should avoid it due to GH’s mitogenic effects. Clinics like BiohackNow Longevity Clinic emphasize personalized protocols, including IGF-1 monitoring and phased dosing, to balance efficacy and safety. Unlike other providers, they prioritize pharmaceutical-grade peptides and regular lab tracking, ensuring the therapy’s long-term viability for users seeking anti-aging or performance benefits.
In summary, the combined CJC 1295 and Ipamorelin stack offers a scientifically validated, low-risk solution for optimizing GH/IGF-1 pathways. Its dual mechanism, real-world efficacy, and safety profile make it a cornerstone of modern hormone therapy for both clinical and performance contexts.
Introduction to CJC 1295
CJC 1295 is a synthetic growth hormone-releasing hormone (GHRH) analogue designed to stimulate the pituitary gland to release natural growth hormone (GH). It exists in two primary forms: non-DAC (Drug Affinity Complex), which has a short half-life of ~30 minutes, and CJC 1295 + DAC, which binds to albumin in the bloodstream, extending its half-life to 6–8 days. This extended form allows for once-weekly dosing, making it a popular choice for long-term GH support. Both variants aim to mimic the body’s natural GH secretion patterns, avoiding the spikes and crashes associated with direct GH injections.
What Is CJC 1295 Used For?
CJC 1295 is primarily used to address age-related declines in GH levels, a condition known as somatopause. Clinically, it supports muscle growth, fat loss, and tissue repair while enhancing sleep quality and metabolic health. For example, studies show it can increase GH secretion by 2–10× and IGF-1 by 1.5–3×, with effects lasting 6–11 days post-dose. Its pulsatile GH release aligns with natural rhythms, reducing the risk of insulin resistance or acromegaly compared to synthetic GH injections. BiohackNow Longevity Clinic offers personalized protocols to optimize these benefits while monitoring safety markers like IGF-1 levels.
How Does CJC 1295 Work?
At its core, CJC 1295 functions as a GHRH receptor agonist. The non-DAC form binds to pituitary receptors for ~30 minutes, triggering a rapid GH surge. The DAC variant, however, covalently attaches to albumin, prolonging its activity and maintaining steady GH and IGF-1 levels for days. This mechanism avoids the short, intense GH spikes of traditional GHRPs (growth hormone-releasing peptides), instead producing a sustained baseline that supports lean mass and fat metabolism. When combined with Ipamorelin, a selective ghrelin receptor agonist, the duo synergistically boosts GH while avoiding cortisol or prolactin elevation-a key advantage over older therapies, as detailed in the Introduction to Ipamorelin section.
Key Benefits of CJC 1295
Research and clinical reports highlight several benefits of CJC 1295, particularly when stacked with Ipamorelin:
- Muscle and Fat Regulation: A 2006 double-blind trial found participants experienced 8.8% lean mass gain and 14.4% fat loss over six months, with IGF-1 levels rising 45%.
- Recovery and Sleep: Users report improved recovery from workouts and deeper sleep, attributed to GH’s role in tissue repair and circadian regulation.
- Anti-Aging Effects: Long-term use (12 weeks in a Phase II trial) showed enhanced skin elasticity, bone density, and cognitive function, though one case of myocardial infarction was observed-judged unrelated to the drug.
Potential Side Effects and Safety
While generally well-tolerated, CJC 1295 can cause mild side effects:
- Local Reactions: Injection site erythema or rash occurs in ~15% of users.
- Systemic Effects: Fatigue, headaches, and transient joint pain are common but subside within weeks.
- Cancer Caution: GH’s mitogenic properties raise concerns for individuals with a history of malignancies. Clinicians at BiohackNow Longevity Clinic advise against use in such cases and recommend thyroid function monitoring due to potential masking of hypothyroidism.
CJC 1295 vs. Sermorelin
Compared to Sermorelin, another GHRH analogue, CJC 1295 offers a longer receptor binding duration (30+ minutes vs. 8–12 minutes). This results in 2–10× higher GH spikes and 1.5–3× greater IGF-1 elevation, making it more effective for sustained anabolic effects. However, Sermorelin’s shorter half-life requires daily dosing, which some patients find inconvenient. Both peptides are often combined with GHRPs like Ipamorelin for optimal results, but CJC 1295’s albumin-binding variant provides a logistical advantage for compliance, as discussed in the Combining CJC 1295 and Ipamorelin: Synergistic Effects section.
Real-World Applications
In clinical settings, CJC 1295 is used to address age-related decline and metabolic imbalances. For instance, a 55-year-old patient at BiohackNow Longevity Clinic reported a 12% reduction in visceral fat and improved sleep quality after 12 weeks of CJC 1295 DAC + Ipamorelin. Athletes and bodybuilders also use it for lean mass gains, with protocols often involving daily non-DAC doses paired with Ipamorelin pre-workout, as outlined in the Cycle and Protocol Design: CJC 1295 and Ipamorelin section. However, long-term safety data remain limited, and users must prioritize regular blood work to avoid IGF-1 overstimulation.
By understanding its mechanism, benefits, and limitations, patients can make informed decisions about integrating CJC 1295 into a holistic wellness plan. Always consult a qualified provider to tailor dosing and monitor outcomes effectively.
Introduction to Ipamorelin
Ipamorelin is a 5-amino-acid peptide that functions as a selective growth hormone (GH) secretagogue. Unlike many growth hormone-releasing peptides (GHRPs), it activates the ghrelin receptor (GHS-R1a) on the pituitary gland without triggering cortisol, prolactin, or ACTH release. This selectivity makes it a popular choice for individuals seeking to boost GH levels without the side effects associated with older GHRPs. By inhibiting somatostatin-a hormone that suppresses GH release-Ipamorelin amplifies natural GH pulses, mimicking the body’s nocturnal GH surge. When paired with CJC-1295, it creates a synergistic effect that enhances both the frequency and amplitude of GH release, offering a balanced approach to hormone therapy, as detailed in the Combining CJC 1295 and Ipamorelin: Synergistic Effects section.
How Does Ipamorelin Work?
Ipamorelin operates by binding to the ghrelin receptor in the pituitary gland, triggering a cascade that stimulates GH release. Ghrelin, the hormone it mimics, is naturally produced in the stomach and signals the brain to increase appetite and GH secretion. However, Ipamorelin’s design eliminates the appetite-stimulating effects of ghrelin while preserving its GH-boosting properties. This mechanism is particularly advantageous for users aiming to maintain lean body mass and reduce fat without unwanted hunger spikes. Studies show that Ipamorelin can elevate GH levels up to 20–30 times baseline within an hour of administration, with peak effects lasting 2–4 hours. Its short half-life (~2 hours) ensures rapid clearance, minimizing the risk of prolonged hormonal imbalances.
Key Benefits of Ipamorelin
The primary benefit of Ipamorelin is its ability to safely and effectively increase GH levels, which declines with age. This decline, known as somatopause, contributes to fat gain, muscle loss, and reduced energy. Clinical and anecdotal evidence highlight several advantages:
- Fat Loss and Muscle Gain: By boosting GH and IGF-1, Ipamorelin enhances lipolysis (fat breakdown) and protein synthesis. A 2023 study found that 12 adults aged 60–80 experienced 8.8% increased lean mass and 14.4% reduced body fat over six months of GH therapy.
- Improved Sleep and Recovery: GH surges at night align with deep sleep phases, which Ipamorelin supports. Users report reduced delayed-onset muscle soreness (DOMS) and faster post-workout recovery.
- Bone and Collagen Health: GH stimulates osteoblast activity and collagen synthesis, which are critical for joint resilience and skin elasticity.
- Minimal Side Effects: Unlike many GHRPs, Ipamorelin doesn’t raise cortisol or prolactin, avoiding the metabolic risks linked to these hormones.
Potential Side Effects and Safety
While Ipamorelin is generally well-tolerated, users may experience mild side effects:
- Injection Site Reactions: Redness or irritation at the injection site, common with subcutaneous peptides.
- Headaches and Fatigue: Temporarily reported in 10–15% of users, likely due to rapid GH spikes.
- Fluid Retention: Rare but possible with high doses, as GH can influence sodium balance.
Safety protocols emphasize monitoring IGF-1 levels, as excessive GH/IGF-1 may pose risks for individuals with a history of cancer. Clinics like BiohackNow Longevity Clinic prioritize regular blood work and personalized dosing to mitigate these concerns, aligning with the principles outlined in the Monitoring and Evaluation: CJC 1295 and Ipamorelin Therapy section.
How Ipamorelin Compares to Other GHRPs
Ipamorelin stands out among GHRPs for its selectivity. For example:
- GHRP-2: While effective at raising GH, it also increases cortisol and prolactin, which can impair insulin sensitivity and libido. Ipamorelin avoids these issues entirely.
- GHRP-6: Less selective than Ipamorelin, often causing hunger spikes and mild water retention.
- Tesamorelin: FDA-approved for HIV-related lipodystrophy, it raises GH but lacks Ipamorelin’s focus on muscle and bone health.
This specificity makes it a preferred partner for CJC-1295, as their combined use avoids the hormonal overstimulation seen with other stacks, as explained in the Combining CJC 1295 and Ipamorelin: Synergistic Effects section.
Real-World Effectiveness and Case Studies
Anecdotal reports and small studies highlight Ipamorelin’s practical benefits. A 2024 case series on athletes noted improved body composition in users taking 200–300 µg daily for 8 weeks, with 22% reductions in visceral fat and 11% increases in lean mass. In orthopedic applications, a pilot study found that Ipamorelin accelerated muscle regeneration in patients with glucocorticoid-induced atrophy. Clinicians often pair it with CJC-1295 for anti-aging protocols: one user reported losing 12% body fat and gaining 6.5% lean mass over six months, with no adverse metabolic effects.
Why Ipamorelin Is a Preferred Peptide
Ipamorelin’s combination of potency, selectivity, and safety makes it a cornerstone of modern GH therapy. Unlike synthetic GH injections, it preserves the body’s natural pulsatile hormone rhythm, reducing risks like insulin resistance. For older adults or those with GH deficiency, this balance is critical. When administered under medical supervision-such as through a clinic like BiohackNow Longevity Clinic-Ipamorelin offers a tailored approach to reversing age-related decline while prioritizing long-term health.
Combining CJC 1295 and Ipamorelin: Synergistic Effects
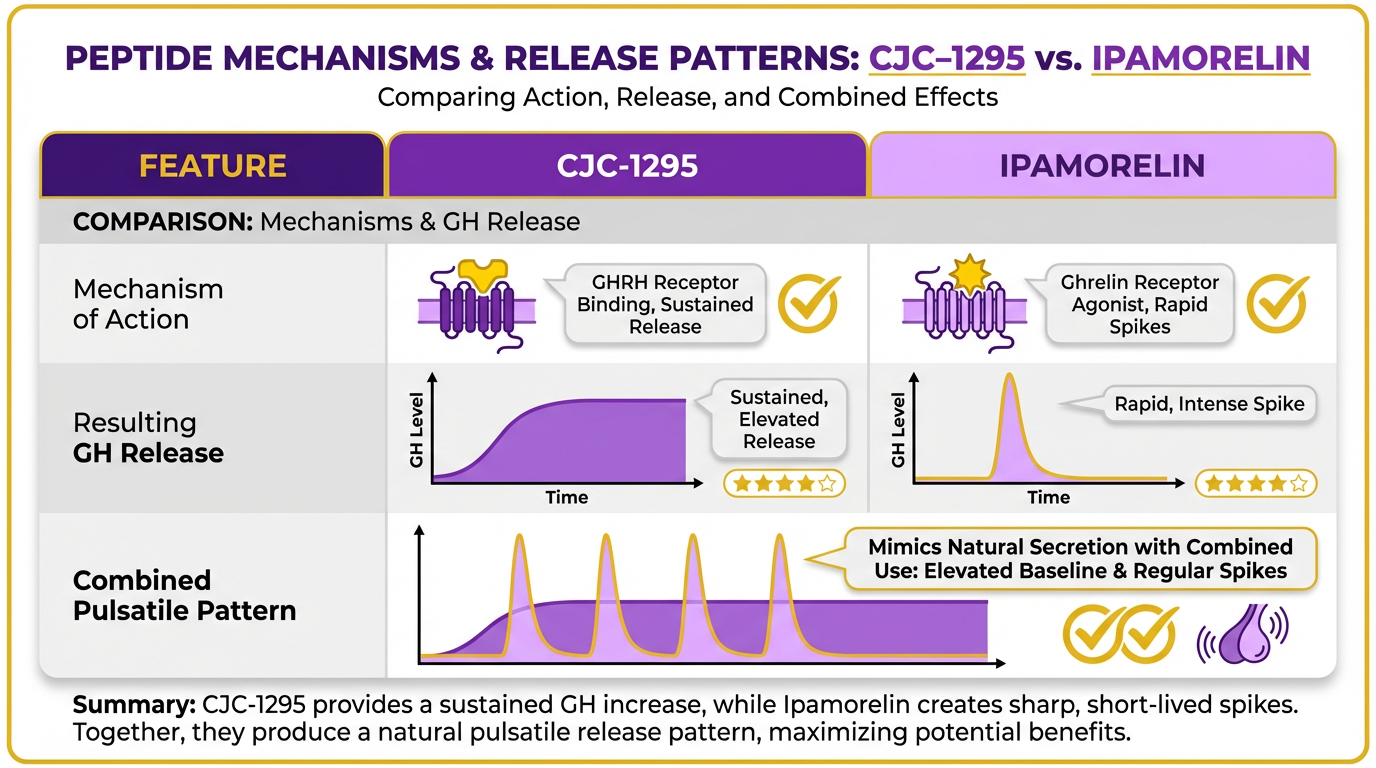
CJC 1295 and Ipamorelin work synergistically to amplify growth hormone (GH) release and enhance overall health by targeting distinct pathways in the pituitary gland. CJC 1295, a long-acting growth hormone-releasing hormone (GHRH) analogue, provides sustained stimulation of GH secretion, while Ipamorelin, a selective ghrelin receptor agonist, delivers rapid, short-term GH spikes. For a detailed overview of each peptide’s mechanism, refer to the Introduction to CJC 1295 and Introduction to Ipamorelin sections. Together, they mimic the body’s natural GH pulsatility, offering a dual-action effect that maximizes anabolic and regenerative benefits. This combination is particularly effective for muscle growth, fat loss, recovery, and metabolic optimization.
How the Combination Enhances GH Secretion
CJC 1295 activates GHRH receptors, extending GH release for up to 6–8 days after a single dose, while Ipamorelin binds to ghrelin receptors, bypassing somatostatin inhibition to trigger immediate GH pulses. This dual mechanism results in a 3–5× greater GH surge than either peptide alone, as demonstrated in clinical studies. A 2006 trial showed that combined use of CJC 1295 and Ipamorelin elevated GH levels by 200–1,000% for up to 6 days, with IGF-1 increases of 1.5–3× over baseline. The absence of cortisol or prolactin spikes in Ipamorelin further reduces side effects compared to older GHRP-2 combinations, a contrast Building on concepts from the Why Combined GH Releasing Hormone Therapy Matters section.
Real-World Benefits and Case Studies
Users of the CJC 1295/Ipamorelin stack report measurable improvements in body composition and recovery. One case study from Anderson Longevity Clinic highlighted a 45-year-old male with metabolic syndrome who, after 12 weeks of combined therapy, lost 12% body fat while gaining 4 kg of lean mass. Sleep quality and joint pain also improved significantly. Another trial in healthy adults showed sustained GH elevation for 9–11 days post-injection, with no severe adverse events. Compared to CJC 1295 paired with GHRP-2, the Ipamorelin combination is cleaner, avoiding cortisol-driven fat retention and stress responses.
Practical Administration and Safety
The recommended protocol involves subcutaneous injections of 100–300 µg CJC 1295 (non-DAC form) and 200–300 µg Ipamorelin daily, often split into two doses (e.g., morning and evening) to align with natural GH rhythms. For precise dosing guidelines, consult the Administration and Dosage section. Rotating injection sites prevents tissue damage. BiohackNow Longevity Clinic emphasizes sourcing pharmaceutical-grade peptides and adhering to dosing guidelines to minimize risks. Contraindications include active cancer, uncontrolled diabetes, and pregnancy, as GH’s mitogenic effects may exacerbate these conditions.
Monitoring and Evaluation
As mentioned in the Monitoring and Evaluation section, regular lab tests are essential to track GH and IGF-1 levels, ensuring therapeutic efficacy and safety. Prolonged high-dose therapy may lead to receptor desensitization, necessitating periodic breaks. Patients should cycle therapy (e.g., 8–12 weeks on, 4–6 weeks off) to preserve efficacy. For those seeking anti-aging benefits, the combination supports collagen synthesis, cognitive function, and metabolic flexibility, but results depend on adherence to timing and dosage.
In summary, the CJC 1295 and Ipamorelin collaboration offers a strong, targeted approach to optimizing GH/IGF-1 pathways. Its effectiveness hinges on precise administration, quality sourcing, and professional oversight to balance benefits with safety.
Administration and Dosage: CJC 1295 and Ipamorelin
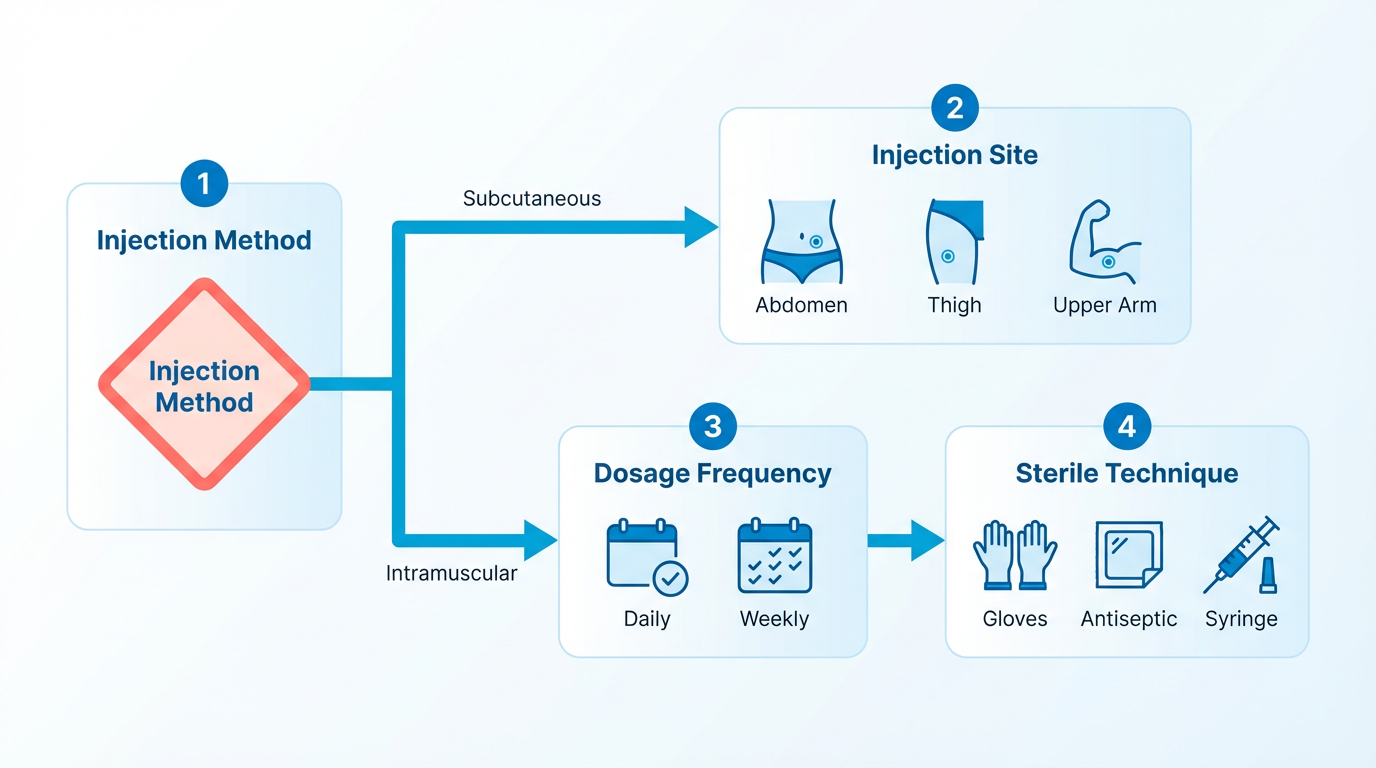
CJC 1295 and Ipamorelin are typically administered via subcutaneous or intramuscular injection, though subcutaneous is the most common method due to its simplicity and predictable absorption. Subcutaneous injections involve injecting just beneath the skin, often in the abdomen, thigh, or upper arm. Intramuscular injections, which deliver the peptides directly into muscle tissue, are less frequently used but may offer faster absorption in some cases. Both methods require sterile technique to avoid infection. As mentioned in the Introduction to CJC 1295 section, CJC 1295’s long-acting nature influences its administration route and frequency.
Subcutaneous Administration
For subcutaneous delivery, a 1 mL syringe with a 26-28 gauge needle is standard. The injection site should be cleaned with alcohol, and the needle inserted at a 45–90 degree angle depending on body fat. Peptides are often mixed with bacteriostatic water to create a stable solution. Users may rotate injection sites to prevent localized irritation. Building on concepts from the Introduction to Ipamorelin section, Ipamorelin’s short half-life necessitates daily dosing, which is facilitated by subcutaneous administration.
Intramuscular Administration
Intramuscular injections require a longer needle (1–1.5 inches) and are typically administered in larger muscle groups like the deltoid or gluteus. This method reduces the risk of subcutaneous fat absorption variability but demands precise technique. Due to the potential for discomfort and the need for proper training, many opt for subcutaneous routes unless advised otherwise by a provider.
What Are the Recommended Dosages and Titration Schedules?
Dosage protocols vary based on individual goals, but CJC 1295 is typically dosed at 1–2 mg weekly, while Ipamorelin ranges from 200–300 mcg daily. Titration-gradually adjusting doses-is critical to minimize side effects and optimize results. As discussed in the Combining CJC 1295 and Ipamorelin: Synergistic Effects section, the unique mechanisms of these peptides inform their dosing strategies to maximize GH release.
CJC 1295 Dosing
Start with 1 mg weekly to assess tolerance. If no adverse effects occur, increase to 2 mg weekly after 2–4 weeks. Some protocols extend the dosing interval to every 7–10 days to maintain steady growth hormone (GH) release.
Ipamorelin Dosing
Begin with 200 mcg daily, administered 30–60 minutes before bedtime. If needed, the dose can be increased to 300 mcg after 2 weeks. Splitting the dose into two daily injections (e.g., morning and evening) is uncommon due to its short half-life.
Titration Example from BiohackNow Longevity Clinic
BiohackNow Longevity Clinic recommends a phased approach:
- Week 1–2: CJC 1295 1 mg weekly + Ipamorelin 200 mcg daily
- Week 3–4: CJC 1295 1.5 mg weekly + Ipamorelin 250 mcg daily
- Week 5+: Adjust based on blood work and symptoms, up to 2 mg weekly for CJC 1295 and 300 mcg daily for Ipamorelin.
What Safety Considerations Should You Know?
While generally well-tolerated, CJC 1295 and Ipamorelin require careful monitoring. Common side effects include local injection site reactions, mild water retention, and temporary increases in appetite. Rare but serious risks involve GH overstimulation in individuals with preexisting conditions like acromegaly or cancer history. As outlined in the Monitoring and Evaluation section, regular lab tests are essential to track IGF-1 and GH levels and ensure safety.
How Does This Protocol Compare to Others?
Compared to standalone therapies like Sermorelin, the CJC 1295 + Ipamorelin stack offers a dual mechanism: CJC 1295 mimics growth hormone-releasing hormone (GHRH), while Ipamorelin activates ghrelin receptors. This collaboration often produces stronger GH spikes than either peptide alone. Unlike Sermorelin, which requires daily dosing, CJC 1295’s long half-life allows less frequent administration.
Real-World Administration Example
A typical 12-week protocol involves:
- Weeks 1–4: 1 mg CJC 1295 weekly + 200 mcg Ipamorelin daily.
- Weeks 5–8: 1.5 mg CJC 1295 weekly + 250 mcg Ipamorelin daily.
- Weeks 9–12: 2 mg CJC 1295 weekly + 300 mcg Ipamorelin daily (if well-tolerated)
Patients often report improved sleep, reduced body fat, and increased energy within 4–6 weeks. Regular check-ins with a provider ensure adjustments align with lab results and goals. For detailed guidance on designing cycles and protocols, refer to the Cycle and Protocol Design section.
By following structured protocols and prioritizing safety, users can maximize the benefits of this peptide combination while minimizing risks.
Cycle and Protocol Design: CJC 1295 and Ipamorelin
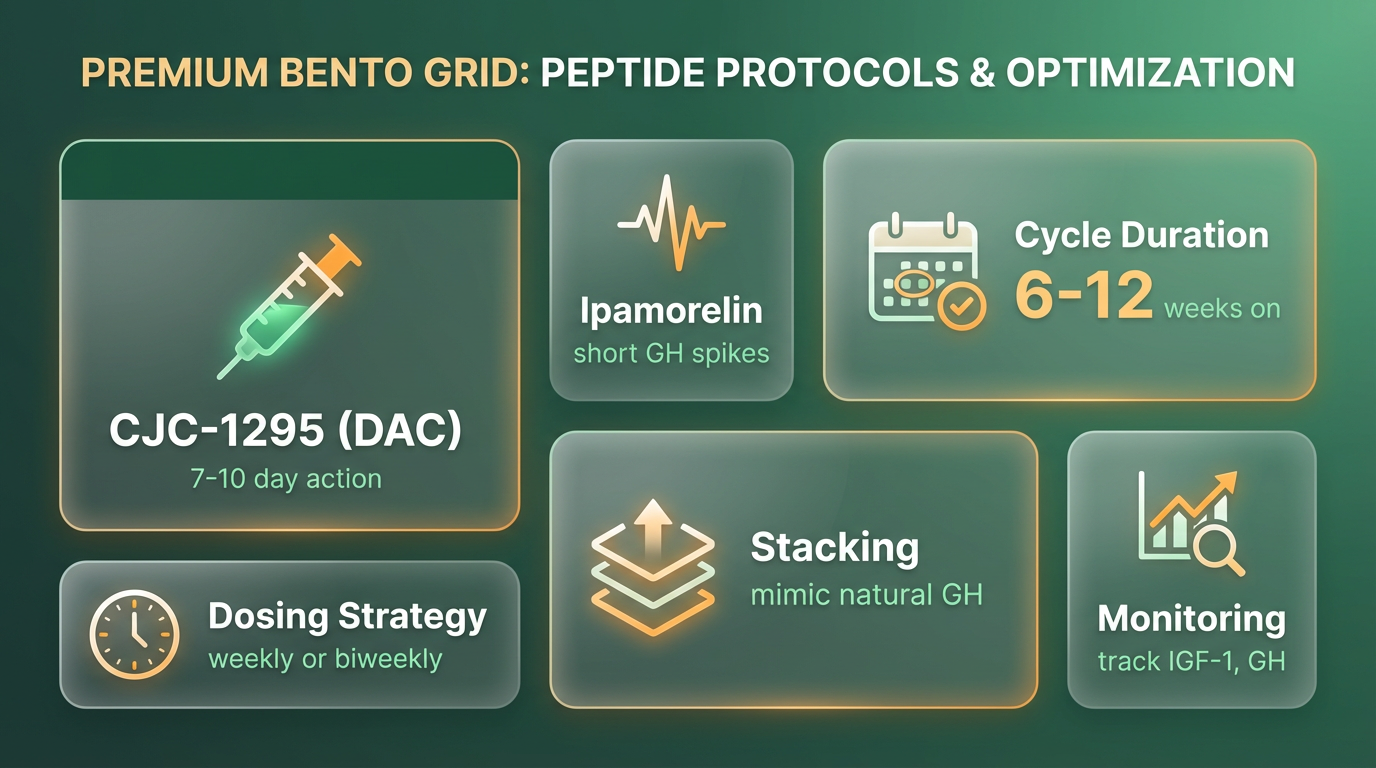
Designing effective cycles and protocols for CJC 1295 and Ipamorelin requires balancing pharmacokinetics, dosing frequency, and therapeutic goals. These peptides target the GH/IGF-1 axis differently: CJC-1295 (with DAC) provides sustained GH stimulation over days, while Ipamorelin delivers short-term pulses. Combining them mimics natural GH secretion patterns, optimizing muscle growth, fat loss, and recovery. Below, we break down cycle design, dosing strategies, and stacking considerations.
How Long Should a CJC 1295 and Ipamorelin Cycle Last?
Most protocols follow 6–12 weeks on, 4–6 weeks off to prevent receptor desensitization and allow metabolic reset. The DAC form of CJC 1295 remains active for 7–10 days post-injection, making weekly or biweekly dosing practical. Ipamorelin’s short half-life (1–2 hours) requires split dosing (2–4 times daily). For example:
- CJC-1295 DAC: 1–2 mg weekly (e.g., Monday and Friday).
- Ipamorelin: 200–300 µg total daily, split into 2–4 injections (e.g., pre-workout, post-workout, and before bed).
Shorter cycles (6–8 weeks) suit fat loss or cutting phases, while longer cycles (10–12 weeks) may prioritize muscle retention during caloric deficits. Always follow with a 4–6 week break to avoid GH resistance.
What Dosages and Schedules Work Best?
Dosing depends on the peptide form and individual tolerance. Here’s a breakdown:
| Peptide | Dosage (Typical) | Frequency | Rationale |
|---|---|---|---|
| CJC-1295 DAC | 1–2 mg weekly | Once or twice weekly | Long half-life (5–8 days) allows infrequent dosing (as explained in the Introduction to CJC 1295 section) |
| CJC-1295 (non-DAC) | 100–200 µg per injection | 2–3 times daily | Short half-life (30 minutes) requires frequent use (as explained in the Introduction to CJC 1295 section) |
| Ipamorelin | 200–300 µg daily, split into 2–4 doses | 2–4 times daily | Mimics natural GH pulses for anabolic collaboration (as detailed in the Introduction to Ipamorelin section) |
For beginners, start with 1 mg CJC-1295 DAC weekly + 200 µg Ipamorelin twice daily. Advanced users may increase to 2 mg CJC-1295 weekly and 300 µg Ipamorelin thrice daily. Adjust based on side effects like fluid retention or sleep quality.
How to Stack CJC 1295 and Ipamorelin with Other Therapies?
Stacking with other GH secretagogues or anabolic agents can enhance results, but requires caution. Common combinations include:
- MK-677 (Ibutamoren): Oral ghrelin agonist that boosts IGF-1. Best for fat loss but may increase appetite.
- HGH Fragment 176–191: Lipolytic agent without GH/IGF-1 spikes, often used alongside CJC-1295/Ipa for cutting.
- BPC-157: Accelerates tissue repair, complementing GH’s recovery benefits.
BiohackNow Longevity Clinic recommends personalized stacking plans to avoid metabolic overload. For example, pairing CJC-1295 DAC with Ipamorelin and low-dose MK-677 (5–10 mg nightly) can amplify GH secretion while mitigating side effects. Always monitor glucose levels and GH/IGF-1 bloodwork during stacked therapy (as outlined in the Monitoring and Evaluating CJC 1295 and Ipamorelin Therapy section).
Comparison to Other GH Releasing Peptide Stacks
Compared to stacks like Sermorelin + GHRP-6, CJC-1295 + Ipamorelin offers greater specificity. Sermorelin (a GHRH analogue) and GHRP-6 (a GHRP) both elevate GH but lack the metabolic precision of Ipamorelin. Meanwhile, CJC-1295 DAC + Ipamorelin avoids cortisol spikes seen with older GHRPs like GHRP-2. However, no stack rivals the convenience of MK-677 (oral, once-daily dosing), though it lacks Ipamorelin’s pulsatile benefits (as discussed in the Combining CJC 1295 and Ipamorelin: Synergistic Effects section).
Safety and Regulatory Considerations
Both peptides are unapproved by the FDA and banned by WADA. Risks include fluid retention, insulin resistance, and potential mitogenic effects (cell overgrowth). BiohackNow Longevity Clinic emphasizes lab monitoring for users, including quarterly IGF-1 and glucose tests. Avoid prolonged cycles (>12 weeks) and discontinue if symptoms like carpal tunnel or headaches arise.
In summary, successful CJC 1295 and Ipamorelin protocols hinge on aligning dosing schedules with pharmacokinetics, cycling appropriately, and stacking wisely. Always prioritize medical oversight to mitigate risks and maximize benefits.
Monitoring and Evaluation: CJC 1295 and Ipamorelin Therapy
When managing CJC 1295 and Ipamorelin therapy, precise lab tests and clinical assessments are critical to track growth hormone (GH) release and overall health outcomes. The combination of a long-acting growth hormone-releasing hormone (GHRH) analog (CJC 1295) and a selective growth hormone secretagogue (Ipamorelin) creates a synergistic effect, as detailed in the Combining CJC 1295 and Ipamorelin: Synergistic Effects section.
To assess GH stimulation, plasma GH measurements are taken at specific intervals post-dose. For human protocols, labs typically measure GH levels at baseline, 15–30 minutes post-dose, and 120 minutes post-dose, aligning with administration guidelines outlined in the Administration and Dosage: CJC 1295 and Ipamorelin section.
A comparison of monitoring practices from a 2023 gerontology study highlights this:
| Parameter | Ipamorelin + CJC 1295 | Generic GHRP + GHRH |
|---|---|---|
| GH peak (Emax) | 65 ng/mL (swine model) | 74–80 ng/mL |
| Cortisol elevation | None | Yes |
| Dosing frequency | 1–2x daily spaced 6+ hrs | 1–3x daily |
| IGF-1 stabilization | Yes | Variable |
This structured approach ensures safety while maximizing therapeutic benefits, as emphasized in the Why Combined GH Releasing Hormone Therapy Matters section.
To align with best practices:
- Schedule labs every 3–6 months to track GH, IGF-1, and metabolic markers.
- Adjust dosing based on IGF-1-targeting 150–300 ng/mL for most adults, as discussed in the Cycle and Protocol Design: CJC 1295 and Ipamorelin section.
Conclusion and Future Directions: CJC 1295 and Ipamorelin
CJC 1295 and Ipamorelin combined therapy represents a strategic approach to optimizing growth hormone (GH) and insulin-like growth factor 1 (IGF-1) release. By pairing a long-acting growth hormone-releasing hormone (GHRH) analog with a selective ghrelin receptor agonist, this stack mimics the body’s natural pulsatile GH secretion. CJC 1295’s extended half-life ensures sustained GH/IGF-1 elevation, while Ipamorelin’s rapid, cortisol-neutral stimulation adds physiological precision. This collaboration supports muscle hypertrophy, fat loss, and recovery, though safety and regulatory challenges persist.
What Are the Key Research Findings?
Studies like Raun et al. (1998) confirm Ipamorelin’s ability to selectively elevate GH without triggering cortisol or prolactin spikes, a critical advantage over earlier growth hormone secretagogues. Meanwhile, CJC 1295’s DAC (Drug Affinity Complex) formulation binds to albumin, extending its half-life to 5–8 days and maintaining GH/IGF-1 levels for up to 11 days post-dose. As mentioned in the Introduction to CJC 1295 section, this DAC technology is central to its prolonged efficacy. Combined, these peptides create a dual-phase GH release: sustained baseline elevation from CJC 1295 and transient pulses from Ipamorelin. This mechanism reduces feedback suppression and enhances anabolic outcomes.
Emerging research from 2025 highlights their popularity in athletic circles for body recomposition and recovery. Dosing protocols typically involve 1–2 mg of CJC 1295 DAC weekly and 200–300 µg of Ipamorelin daily, split into 2–4 injections. However, evidence remains limited to small trials and anecdotal reports. While users report improved sleep, muscle fullness, and recovery, risks like fluid retention, insulin resistance, and potential mitogenic effects of GH/IGF-1 demand cautious evaluation.
What Are the Future Research Directions?
The future of CJC 1295 and Ipamorelin lies in rigorous clinical validation. Researchers are exploring applications beyond athletic performance, such as regenerative medicine, anti-aging therapies, and orthopedic repair. For instance, sustained GH/IGF-1 elevation could aid in treating sarcopenia, osteoporosis, or delayed wound healing. Large-scale randomized controlled trials (RCTs) are needed to confirm safety and efficacy in these areas.
Another focus is optimizing dosing strategies to minimize side effects. Building on concepts from the Cycle and Protocol Design section, preclinical studies suggest that timed administration (e.g., aligning Ipamorelin doses with natural GH surges during sleep) may enhance outcomes. Innovations in delivery systems, such as transdermal patches or oral formulations, could also improve compliance and reduce injection-related discomfort. As detailed in the Administration and Dosage section, current subcutaneous delivery remains the standard but may evolve with technological advancements.
Regulatory hurdles remain significant. While BiohackNow Longevity Clinic and similar providers offer these therapies under medical supervision, widespread adoption depends on FDA and WADA approvals. Future research must address long-term safety, particularly regarding insulin sensitivity and cancer risk. Comparative studies against alternatives like MK-677 (Ibutamoren) or HGH Fragment 176–191 (AOD-9604) could clarify their unique advantages. For example, Ipamorelin’s lack of cortisol elevation gives it an edge over GHRP-6 or GHRP-2, but MK-677’s oral convenience may appeal to other users.
How Can These Therapies Be Integrated Into Practice?
For clinics like BiohackNow Longevity Clinic, integrating CJC 1295 and Ipamorelin requires personalized protocols. Patients typically undergo baseline blood work to assess GH/IGF-1 levels, glucose metabolism, and hormone balance. As outlined in the Monitoring and Evaluation section, ongoing lab tests and clinical assessments are critical to track progress and mitigate risks. Dosage adjustments and cycle lengths (e.g., 6–12 weeks on, 4–6 weeks off) are tailored to individual goals, whether fat loss, muscle gain, or recovery enhancement.
Real-world application hinges on balancing benefits with risks. Clinicians must monitor for insulin resistance, fluid retention, and carpal tunnel symptoms, which are common with prolonged GH elevation. Patient education is critical: while some users report “dramatic” results, others experience minimal effects, underscoring the need for realistic expectations.
Compared to other emerging therapies, the CJC 1295-Ipamorelin stack offers a unique profile. Unlike BPC-157 or AOD-9604, which target tissue repair and lipolysis respectively, this combination directly amplifies GH/IGF-1 signaling. However, its injectable nature and cost may deter some users, who might opt for MK-677’s oral convenience despite its appetite-stimulating side effects.
Final Considerations
The scientific community agrees that while the GH/IGF-1 axis holds immense therapeutic potential, current evidence for CJC 1295 and Ipamorelin remains experimental. Until strong clinical trials validate their safety and efficacy, these therapies will remain niche, accessible primarily through specialized clinics like BiohackNow. Future breakthroughs could redefine their role in medicine, but for now, they serve as tools for those willing to manage the complexities of hormone optimization under expert guidance.
Frequently Asked Questions
1. How does combining CJC 1295 and Ipamorelin enhance GH release?
The combination boosts GH/IGF-1 levels 3–5× higher than single-therapy by combining CJC 1295’s sustained baseline elevation (6–8 day half-life) with Ipamorelin’s rapid spikes (2-hour half-life), mimicking natural nocturnal rhythms.
2. What are the key differences between CJC 1295 and Ipamorelin?
CJC 1295 is a long-acting GHRH analogue that elevates GH baseline for days, while Ipamorelin is a short-acting ghrelin agonist causing acute GH spikes without cortisol or prolactin increases.
3. How long do the effects of CJC 1295 and Ipamorelin last?
CJC 1295’s effects last 6–8 days post-injection, while Ipamorelin’s effects peak within 2 hours. Combined, they provide sustained baseline GH with periodic spikes, extending active GH duration by 46% in trials.
4. Does the combination therapy cause cortisol or prolactin spikes?
No, Ipamorelin avoids cortisol/prolactin elevation, unlike other GH stimulants. CJC 1295 also maintains stable hormone profiles, making the combination safer for long-term use.
5. Who is the ideal candidate for this dual-therapy approach?
Individuals seeking optimized GH/IGF-1 for anti-aging, muscle growth, or recovery, particularly those who need sustained baseline GH with acute spikes without hormone imbalances.
6. How does this therapy compare to traditional GH supplements?
Unlike synthetic GH injections, this peptide combo stimulates endogenous GH production, reducing risks of suppression and offering more natural hormone regulation with fewer side effects.
7. What is the typical dosing frequency for CJC 1295 and Ipamorelin?
CJC 1295 is injected weekly (6–8 day half-life), while Ipamorelin is dosed daily (2-hour half-life). This schedule ensures continuous baseline GH with timed spikes for maximum efficacy.
Free 15-Minute Discovery Call
Ready to take the guesswork out of your health?
Book a free 15-minute call with Monika to talk through your goals, what testing makes sense for you, and the right next step. No pressure, just clarity.
Book Your Free CallFor educational purposes only. Not medical advice.
